Your baby has two ages on paper. One starts on the day they were born. The other starts around the day they were due. Which one should you use when someone asks about naps, first foods, growth or milestones?
Use corrected age as developmental context after a premature birth, but do not use it for everything. Sleep expectations, early skills, play and some growth-chart readings may be interpreted using corrected age. Routine vaccinations start from time since birth, while fever and medicine decisions need current professional guidance based on the baby's actual age, weight, health and product instructions.
> Corrected age is a fairer comparison, not a deadline and not a diagnosis.
Corrected age in 30 seconds
Chronological age is time since birth. Corrected age, also called adjusted age, is time since the original due date.
You can calculate it in either of two ways:
`corrected age = chronological age − number of weeks early`
or simply count forward from the estimated due date.
| Example | Chronological age | Born early | Corrected age | |---|---:|---:|---:| | Baby born at 32 weeks | 18 weeks since birth | 8 weeks | About 10 weeks | | Baby born at 28 weeks | 7 months since birth | 12 weeks | About 4 months | | Baby has not reached their due date | 6 weeks since birth | 10 weeks | Not yet term-equivalent |
The Bliss premature-baby weaning guide uses the same due-date definition. Dates can be revised during pregnancy, so use the estimated due date recorded by your maternity or neonatal team rather than reconstructing one from memory.
Which age should I use?
This is the quick reference worth saving:
| Decision | Age to start with | What matters too | |---|---|---| | Early milestones and play ideas | Corrected age | The baby's own progress and any neonatal follow-up plan | | Sleep expectations and wake-window guidance | Corrected age as a gentler starting point | Actual sleep history, cues, feeding and health | | Growth centiles | Corrected age where the appropriate chart or clinician uses it | Gestation, measurement quality and the trend, not one dot | | Starting solids | Corrected-age range plus readiness | Feeding skills and individual neonatal/dietetic advice | | UK vaccinations | Chronological age | The national schedule and neonatal team's instructions | | Fever, medicine suitability and doses | Actual age and current clinical/product advice | Weight, medical history, symptoms and the exact medicine |
There is no single switch that makes one age “real” and the other irrelevant. The purpose of the question determines the useful clock.
Corrected age and premature-baby sleep
A baby born eight weeks early has had eight fewer weeks to mature before birth. Comparing their naps with a term baby of the same birth-date age can make ordinary, younger sleep look like a problem.
Corrected age can therefore be a kinder starting point for:
- broad awake-time expectations
- the likely number and shape of naps
- how much day-to-day rhythm to expect
- whether a sleep change may sit alongside a new developmental skill
- age-framed settling suggestions
It is still only context. There is no clinically exact wake-window prescription for every baby, and premature babies may also have reflux, feeding plans, respiratory needs or follow-up instructions that generic sleep advice cannot account for.
Use the baby's real pattern before an internet timetable. Look at several ordinary days: when sleep actually began, how long it lasted, what happened after feeds and how the baby behaved, not whether a chart said the nap should have happened at 10:12.
Before the due date
Before term-equivalent age, do not force a “newborn routine” simply because several weeks have passed since birth. Feeding and medical plans from the neonatal team lead. Sleep may be fragmented, and a baby who is difficult to wake for feeds, unusually floppy, breathing differently or feeding much less needs professional assessment, not schedule troubleshooting.
Safer-sleep guidance still applies. Put baby on their back in a clear, flat, separate sleep space and follow any extra advice given because of prematurity or medical needs.
Corrected age and milestones
Bliss says premature babies' development should be assessed from their due date. That prevents an eight-week-early baby being treated as “late” for not performing like a baby who had eight more weeks of development before birth.
Use corrected age to choose suitable play and to frame conversations about rolling, reaching, sitting, babbling and social interaction. Then watch the child, not a countdown:
- offer short, calm floor-play opportunities while awake
- notice attempts and progress rather than only completed milestones
- avoid forcing a position or drilling a skill
- mention concerns without waiting for a milestone window to expire
Corrected age must not be used to dismiss a loss of skills, persistent stiffness or floppiness, marked asymmetry, unusual movements, feeding difficulty or reduced responsiveness. Speak with your health visitor, neonatal team, physiotherapist or GP whenever you are worried.
Corrected age and growth charts
Growth needs the right reference. The Royal College of Paediatrics and Child Health's Neonatal and Infant Close Monitoring chart is designed for very preterm infants and children needing close monitoring from 23 weeks' gestation to two years' corrected age.
That does not mean parents should diagnose growth from a centile calculator. A useful growth review considers:
- whether weight, length and head circumference were measured accurately
- the gestation and due date used for plotting
- the pattern across time
- feeding, illness and the baby's wider health
- which chart the clinical team considers appropriate
Before a very premature baby reaches their due date, comparing them directly with a term-newborn curve can create a misleadingly low result. If an app cannot make a valid comparison, showing no centile is safer than manufacturing one.
Corrected age and starting solids
For most term babies, NHS guidance says solid foods begin from around six months when the three readiness signs appear together. Premature-baby weaning needs more individual interpretation.
Bliss advises looking at developmental readiness as well as corrected age, not starting from birth-date age alone. A baby should be able to:
- stay in a stable, supported upright position with good head control
- coordinate looking, reaching, grasping and bringing food towards the mouth
- swallow food rather than automatically pushing it back out
The Bliss guide also recommends individual support when a baby was very ill on the neonatal unit or has continuing medical, feeding or developmental needs. Your neonatal dietitian, speech and language therapist, health visitor, paediatrician or GP may set a different plan.
Do not turn this into “exactly six months corrected for every premature baby.” Readiness is not one checkbox, and an age calculator cannot assess swallowing, posture or clinical nutrition needs. Milk remains central while first tastes and textures are introduced alongside it.
When chronological age still leads
Corrected age is developmental context. It must not accidentally delay age-based protection or make an unsafe treatment seem suitable.
Vaccinations
The UK Health Security Agency's Green Book says premature infants should receive immunisations at the appropriate chronological age, counted from their date of birth, according to the national routine schedule. Prematurity is not a reason to postpone them unless the clinical team gives a specific instruction.
Fever and medicines
The NHS fever guidance says to call NHS 111 or a GP urgently when a baby under three months old has a temperature of 38°C or higher. It also lists minimum ages and other restrictions for common medicines. Use the baby's actual age for that age band; do not subtract prematurity and improvise a different threshold.
Never calculate a dose from corrected age. Check the exact label or prescription and ask a pharmacist, GP, neonatal team or NHS 111 when unsure. Weight, dehydration, asthma, other medicines and medical history can change what is appropriate.
When do you stop correcting age?
Many UK developmental services use corrected age through roughly the first two years. One NHS neonatal therapy service explains that it generally corrects motor development until two years corrected age, when the difference often matters less.
That is a practical convention, not a birthday on which every child suddenly “catches up.” Growth-chart methods and specialist follow-up may use correction differently. Ask the team following your child what they use and why.
A good transition is gradual: give increasing weight to the child's observed pattern and clinical review instead of flipping from corrected to chronological expectations overnight.
How the real OBubba app handles two ages
The current native app stores the date of birth and estimated due date separately. When those dates show that a baby arrived at least three weeks early, it uses corrected age where developmental timing is the useful frame. This includes sleep guidance, schedule predictions, play ideas, development windows, milestone context and early weaning screens.
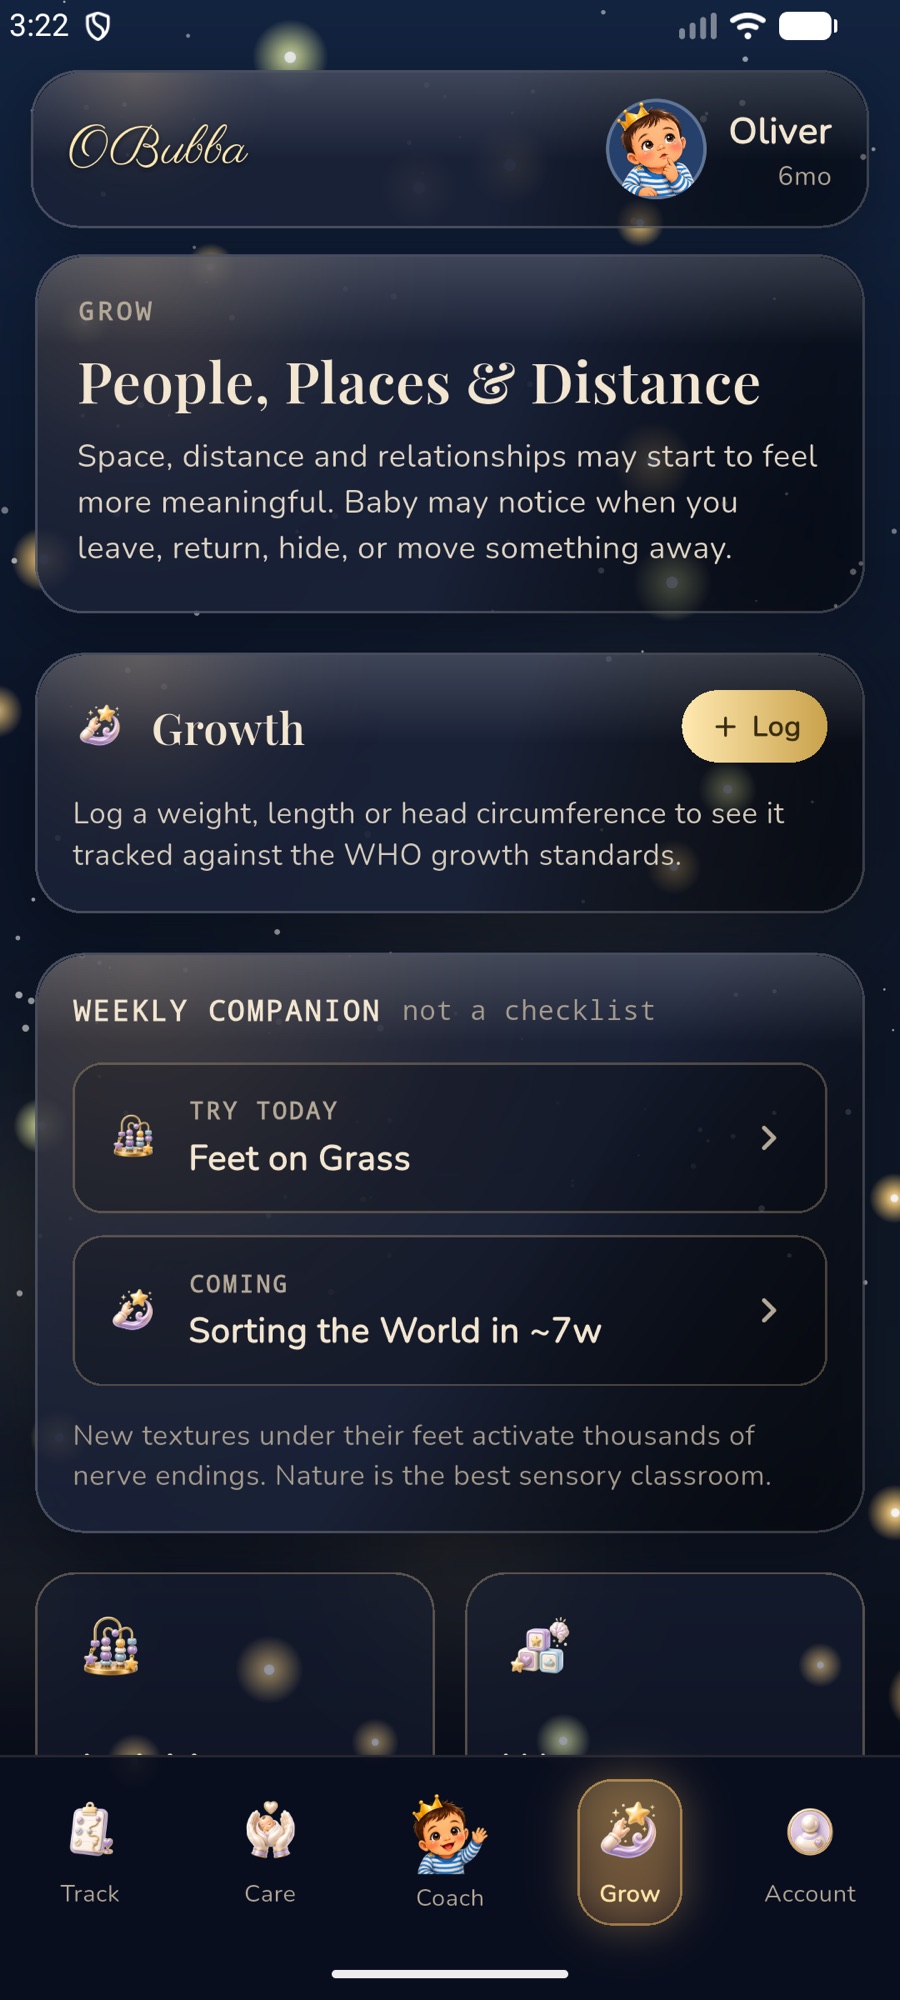
Growth readings use the corrected date where applicable and withhold a percentile when the comparison would be invalid, such as before term-equivalent age. Developmental guidance begins handing back towards chronological age gradually near age two instead of changing the baby's guidance in one abrupt overnight jump.
The safety boundary is separate in code: fever checks and medicine-age suitability continue to use actual chronological age. Corrected age is never allowed to make an age-restricted medicine look suitable.
OBubba can organise and personalise context; it cannot determine feeding readiness, diagnose delay, interpret a sick baby or replace a neonatal plan. If the due date is missing or wrong, the guidance cannot correct itself, so check both dates in the child's profile.
Keep both ages in one shared record →
Track sleep, feeds, growth, development and weaning together, with age-aware guidance that respects a premature baby's timeline.
A calm setup checklist
Before relying on any baby app after premature birth:
- enter both the exact date of birth and estimated due date
- record gestation once and keep it consistent
- add the clinical team's feeding, medicine and follow-up instructions outside any generic schedule
- share access with the adults who log care so dates and doses are not duplicated
- bring trends and questions, not app verdicts, to appointments
- correct a mistaken date rather than “compensating” by editing sleep or milestone logs
Keep both ages available when speaking with a professional: “14 weeks since birth, 6 weeks corrected” is clearer than saying only “about three months.”
Frequently asked questions
Is corrected age the same as adjusted age?
Usually, yes. Both mean age calculated from the original due date after a premature birth. Some professionals may also discuss gestational or post-menstrual age, especially around the neonatal period; ask which measure they mean if the wording is unclear.
My baby was only two weeks early. Should I correct their age?
Usually not for everyday developmental expectations. Correction is mainly used after preterm birth, but practices vary by gestation and purpose. Ask your health visitor or neonatal team if your baby has specific follow-up needs.
Should a premature baby start solids at six months chronological or corrected?
Neither date should act alone. Use corrected-age framing, the baby's combined readiness signs and individual professional advice, especially after very early birth, illness, feeding difficulty or delayed motor development.
Should vaccinations be delayed until corrected age?
No. UK guidance schedules premature infants by chronological age unless their clinical team gives a specific instruction.
What age should I tell nursery or family?
Give both when it is useful: “eight months from birth, six months corrected.” Explain that feeds, medicines and safety instructions are not to be changed by subtracting the weeks early.
Does corrected age mean my baby is behind?
No. It removes weeks the baby did not have in the womb before birth, creating a fairer developmental comparison. It does not predict an individual outcome or guarantee when a skill will appear.
Sources and support
- Bliss: Early developmental milestones
- Bliss: Weaning your premature baby
- RCPCH: Neonatal and Infant Close Monitoring growth charts
- UKHSA: Childhood vaccinations for parents of premature babies
- NHS: Fever in children
This UK-oriented article is general information, not medical advice, a developmental assessment or an individual feeding or sleep plan. Follow the instructions from your baby's neonatal and community teams. Contact your health visitor, neonatal team, GP or NHS 111 when concerned; call 999 in an emergency.
Ready to try OBubba?
Use OBubba to track feeds, sleep, naps, nappies, growth, milestones and family handovers in one calm baby tracker app.