You warm the milk, settle into a quiet chair and offer the bottle. Your baby turns away. You try again; their back arches and the crying begins. If childcare or a return to work is approaching, a rejected teat can feel much bigger than one unfinished feed.
Bottle refusal is common when a breastfed baby is learning a new feeding method, but a baby who previously fed well and suddenly refuses deserves a different level of attention.
The first rule is not to force the teat or chase your baby's mouth. Stop the attempt, calm everyone, make sure your baby is still taking milk another way and practise again when they are calm—not ravenously hungry. Pressure can turn an unfamiliar skill into a repeated battle.
What to do at the next bottle attempt
Keep the next practice deliberately small:
- Choose a calm, awake moment. Do not wait until your baby is exhausted or crying hard with hunger.
- Ask another familiar carer to try. Some breastfed babies accept a bottle more readily when the breastfeeding parent is not holding them. This is an experiment, not a rule.
- Hold baby close and semi-upright. Keep their head supported and their face visible.
- Invite rather than insert. Touch the teat to the upper lip and wait for your baby to open their mouth.
- Keep the bottle almost horizontal. Let milk flow slowly and give your baby pauses.
- Stop at refusal cues. Turning away, pushing the bottle, stopping sucking, spilling milk or becoming distressed means pause or finish.
- Record what actually happened. “Offered 60ml; took 15ml calmly from Dad” is more useful than “failed again”.
The NHS mixed-feeding guidance advises trying the bottle when a baby is calm and happy because tired or hungry babies are less likely to accept something new. The NHS also recognises that a successfully breastfed baby may initially refuse a bottle and recommends going slowly at the baby's pace.
Is this learning—or a sudden feeding problem?
Start by separating two situations.
Baby has never accepted a bottle
This is usually a new-skill problem. The teat feels, smells and behaves differently from a breast. The milk may arrive before your baby expects it, or not arrive as quickly as they want. Short, pressure-free practice is appropriate while milk intake continues through breastfeeding or another clinically agreed route.
Baby used to take bottles and suddenly refuses
Look for what changed:
- a blocked nose or illness
- teething or mouth pain
- thrush, ulcers or another oral problem
- a different teat, bottle, milk temperature or formula
- flow that feels too fast or too slow
- coughing, choking, gulping or dribbling during feeds
- vomiting or distress after feeds
- long gaps that leave baby frantic before the bottle arrives
- a negative experience such as pressure or a very fast feed
Sudden refusal is not something to solve only by buying another bottle. If your baby is refusing their usual source of milk, seems in pain or is unwell, speak to a health professional promptly.
What bottle-refusal cues look like
Refusal is communication. It may look like:
- keeping the mouth closed
- turning the head away
- pushing the teat out with the tongue
- pushing the bottle or carer's hand away
- taking a few sucks, then repeatedly stopping
- arching, crying or becoming tense as the bottle approaches
Some behaviours point more towards the feeding mechanics than refusal itself:
| What happens | What may be worth checking | Next step | |---|---|---| | Milk spills from the mouth; baby coughs or gulps | Flow may be too fast, or coordination is difficult | Lower the bottle, pause and seek feeding advice if repeated | | Baby sucks hard but becomes frustrated | Flow may be too slow or the teat may collapse | Check the teat and vacuum; ask a professional before making large changes | | Baby accepts a little, then turns away calmly | They may need a break or be finished | Respect the cue; do not pursue the missing millilitres | | Baby cries as soon as the feeding position begins | The routine may predict pressure, or there may be pain | End the attempt and get help if this repeats | | Baby refuses bottle but breastfeeds normally | Bottle skill, carer or timing may be the issue | Practise calmly while protecting normal milk intake | | Baby refuses breast and bottle | Illness, pain or another feeding problem needs consideration | Seek prompt professional advice |
The NHS bottle-feeding guide lists turning the head away, pushing the bottle, stopping sucking and spilling milk as cues that a baby needs a break or has had enough.
Use paced, responsive bottle feeding
Paced feeding gives your baby more control over the flow and the decision to continue.
- Hold your baby close in a semi-upright position.
- Touch the teat to the upper lip and wait for an open mouth.
- Hold the bottle almost horizontal, tipped only enough to keep milk in the teat.
- Watch your baby's face and hands rather than the ounce markings.
- Lower the bottle to pause the flow when your baby needs a break.
- Burp when needed.
- End the feed when your baby shows they are done.
Never prop a bottle or leave a baby feeding alone. Do not feed a baby while they are inside a sling or carrier.
Pacing does not guarantee acceptance. It removes some common reasons a baby may feel overwhelmed by a bottle and keeps the adult responsive when only a small amount is taken.
Should someone else offer the bottle?
It is worth testing. A baby held by the breastfeeding parent may reasonably expect the breast. A partner, grandparent or nursery carer brings different cues.
Keep the rest familiar: the same quiet room, close hold and low-pressure invitation. The breastfeeding parent might leave the room briefly, but does not need to disappear from the house or tolerate prolonged crying.
If another carer succeeds, write down the useful detail:
- which position they used
- whether there was gentle movement
- what time it was
- how hungry and tired baby seemed
- teat and flow
- milk temperature
- how much was actually taken
“Dad is better at bottles” is less transferable than “upright by the window, 20 minutes after waking, slow flow, took 45ml.”
Do you need a different bottle or teat?
Sometimes a teat change helps, but constant equipment switching can make the test impossible to read.
Choose one bottle and teat that are suitable for your baby's age and feeding needs. Try them for several calm attempts before changing one variable. A faster flow is not automatically better; coughing, gulping and spilling can mean milk is arriving too quickly. A flow that is too slow can also lead to frustration.
If your baby dribbles heavily, repeatedly pushes the teat out, feeds for a very long time, coughs, chokes or cannot manage even a slow flow, ask for a feeding assessment. The NHS tongue-tie guidance notes that these can be feeding-difficulty signs, but they do not prove tongue-tie.
Do not cut or enlarge a teat hole yourself.
What about milk temperature and taste?
Some babies accept milk at one temperature and reject it at another. If using expressed milk, a baby may also react to differences in smell or taste after refrigeration or freezing.
You can test milk at a safe, comfortably warm or room temperature, following storage and warming guidance. Never microwave milk because it can create hot spots. Always prepare formula exactly as directed; do not change the powder-to-water ratio to alter taste.
Change temperature once while keeping the teat, carer and timing steady. That turns guessing into a useful experiment.
A four-day practice plan before childcare
If bottle feeding becomes essential in four days, this plan keeps the practice calm and structured. It cannot guarantee acceptance by day four. If you have longer, begin a week or two beforehand and spread the practice more gently.
Day 1: make the bottle neutral
Let your baby see and touch the bottle during a calm awake period. Offer a small amount without expecting a full feed. Stop when they turn away.
Day 2: change the person, not everything
Ask another familiar adult to offer the same bottle in a comfortable semi-upright position. The breastfeeding parent can step away. Keep the attempt short.
Day 3: test timing
Offer when baby is calm and lightly hungry—perhaps after waking, before they become frantic. Keep the carer and equipment the same.
Day 4: rehearse the real handover
Let the future carer offer the bottle in the place and approximate rhythm they will use. Share your baby's hunger, break and finished cues. Record the amount taken, not the amount prepared.
If an attempt becomes tense, return to normal feeding and try another day. Protecting intake and the feeding relationship matters more than completing the schedule.
Returning to work when baby still refuses
Bottle acceptance is not a moral requirement for childcare. Depending on age, development and individual advice, a health visitor or feeding specialist may discuss other ways to offer milk. Do not improvise with cups, syringes, thickened feeds or solids as a substitute for milk without appropriate guidance.
Before the first day, give the carer:
- your baby's early hunger cues
- signs they need a break
- their usual position and teat
- safe milk storage and preparation instructions
- permission to stop rather than force
- the number for contacting you
- clear escalation instructions if intake is low or nappies reduce
Use OBubba's shared-care guide so the carer records the same timeline rather than sending a second, disconnected list.
Track intake without turning practice into a quota
Three numbers are often confused:
- Prepared: how much milk was placed in the bottle.
- Offered: the bottle was presented to the baby.
- Taken: how much milk actually left the bottle and was swallowed.
Only the third belongs in an intake total. If you prepared 90ml and 70ml remains, log 20ml taken. Add a short note if useful: “calm attempt; turned away after 5 minutes.” If nothing was taken, use a standalone note rather than logging a zero-volume feed that could inflate feed counts.
Also watch:
- breastfeeding or other milk feeds
- wet and dirty nappies
- vomiting or distress
- feeding duration and repeated coughing
- general alertness and wellbeing
- growth measured appropriately over time
One low bottle does not define daily intake in a combi-fed baby. Bottle millilitres cannot measure milk transferred at the breast.
How OBubba supports bottle refusal
In the current app, open Track → Feed → Bottle to record the time and amount actually taken in ml or oz. Add a concise note for context. The unit toggle converts an amount already entered, so changing from ml to oz does not silently change the meaning of the number.
Bottle feeds sit on the same timeline as breastfeeds, pumping sessions, wet nappies, sleep and growth. That matters for mixed feeding: OBubba deliberately suppresses a bottle-only low-intake judgement when a breastfeed is also logged that day, because the breast portion is unmeasured.
For a baby with a genuine bottle-feeding history, the feeding engine can compare measured daytime intake with age and time of day. It waits until at least six waking hours have passed and requires at least three measured bottle feeds across the prior week before treating bottle volume as a usable history. It also suppresses that bottle-only judgement when a breast or combined feed is logged that day, because the breast portion is unmeasured. Wet-nappy safety checks remain separate.
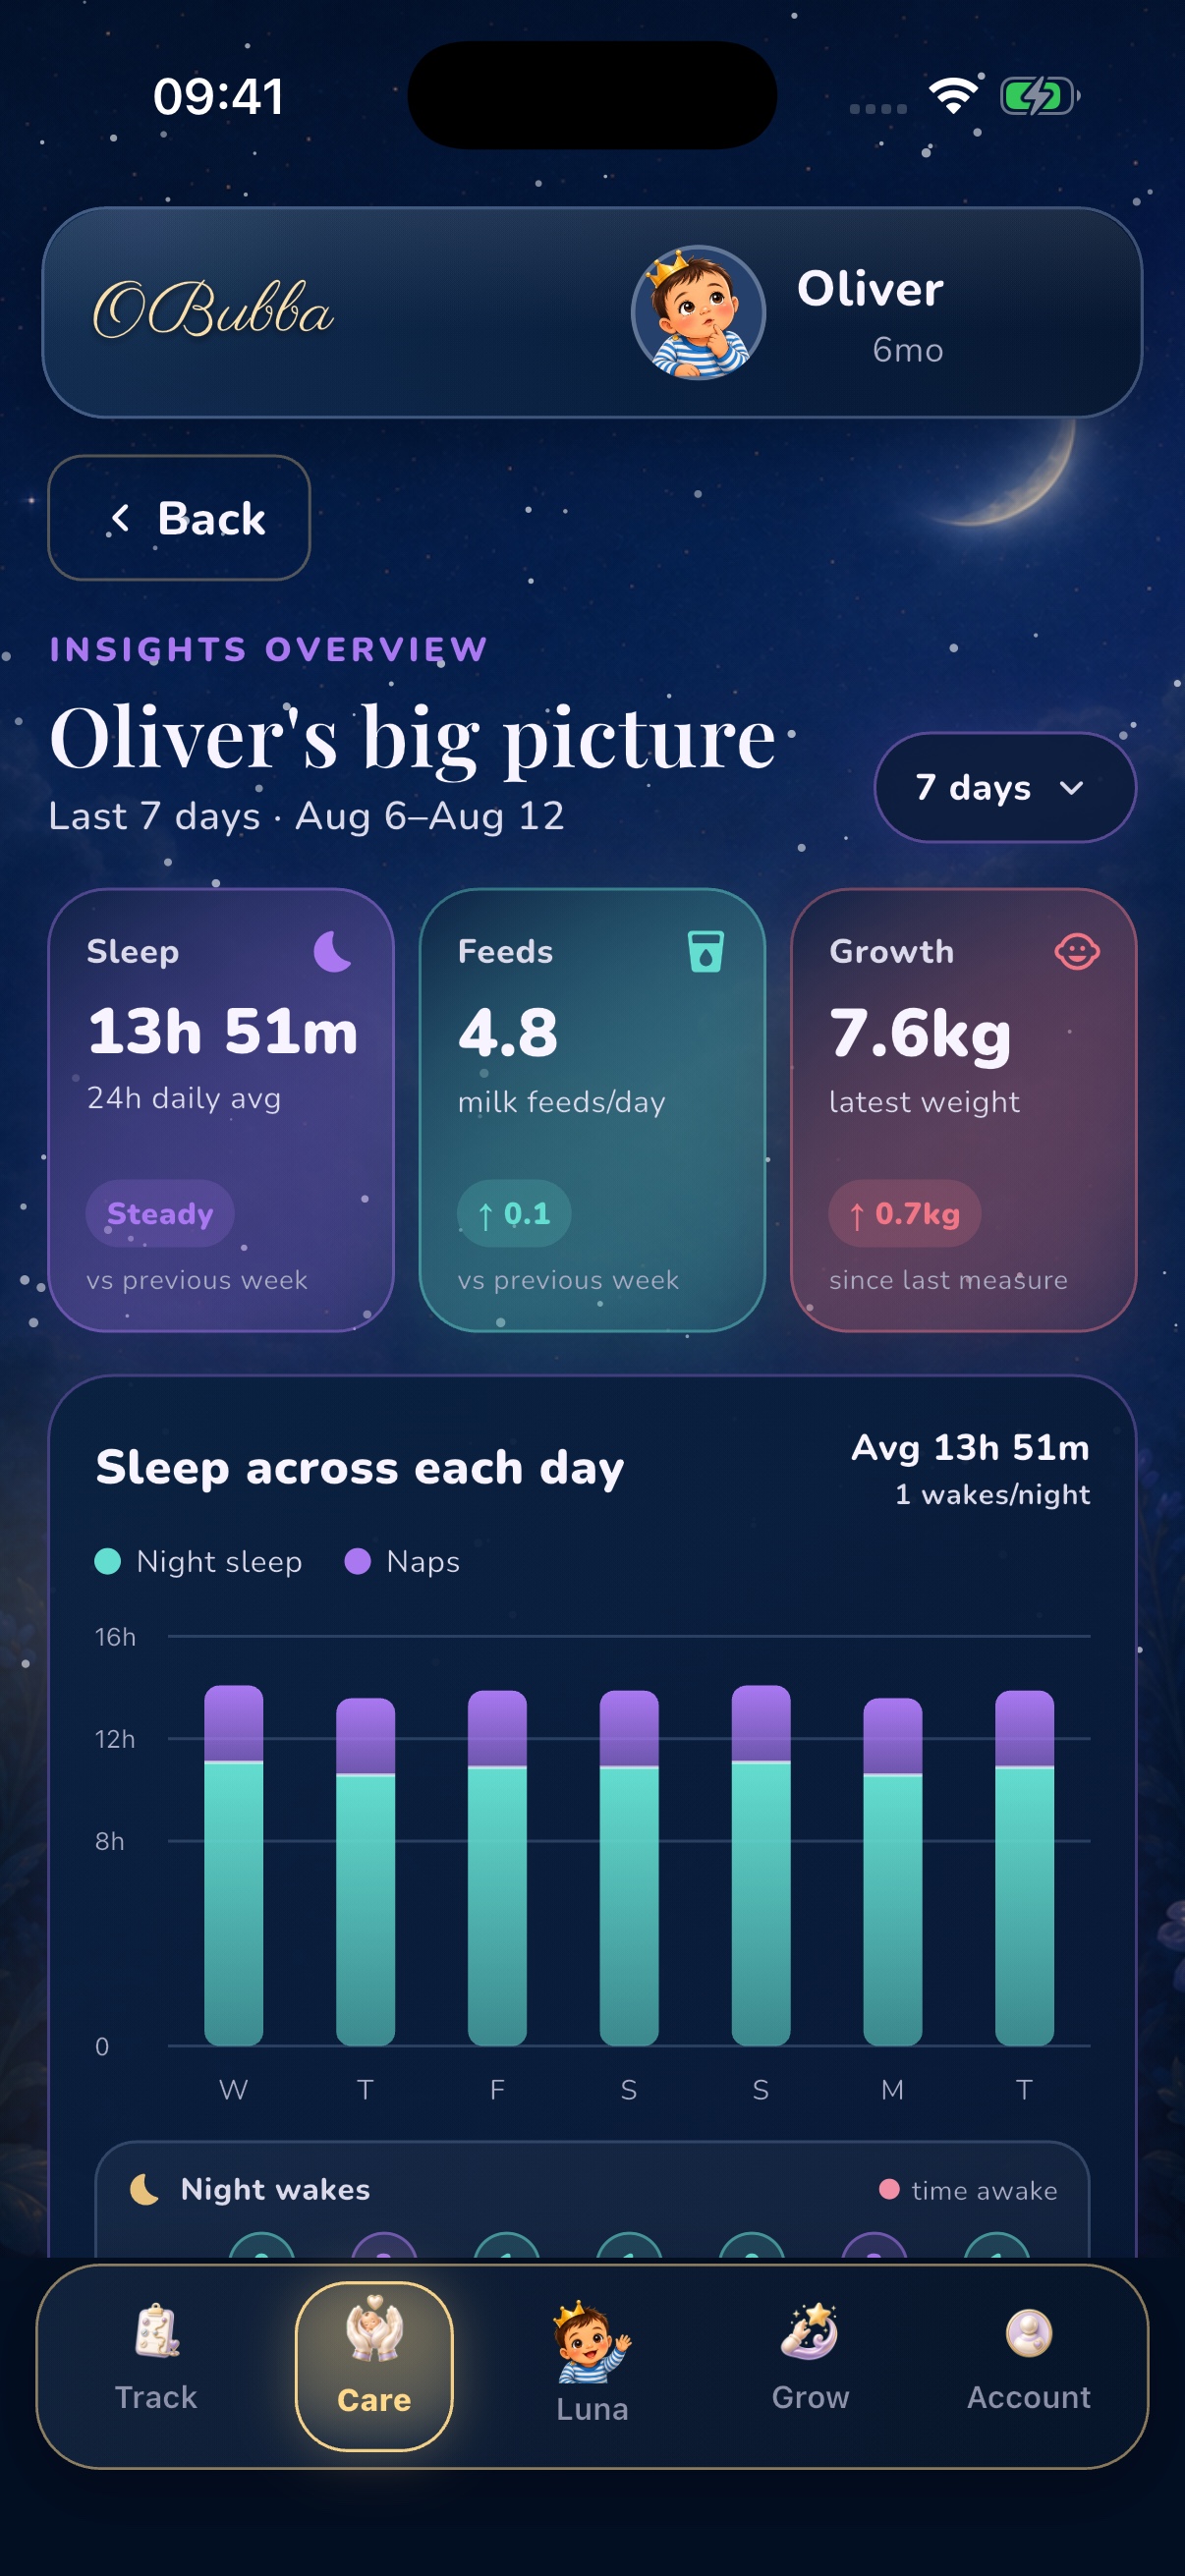
The Insights Overview can show average milk feeds per day beside the latest growth entry, while reports help turn the week into a clearer health-visitor conversation.
Ask Bubba Coach about bottle refusal and the app routes to its specific bottle-refusal guidance rather than a generic feeding answer. It suggests a calm, lightly hungry attempt, another familiar carer and short pressure-free practice. The Coach cannot inspect oral function, diagnose pain or know how much milk transferred unless you log it.
Bottle, breast, pumping and nappy logs, along with the Insights Overview and reports, remain available without Premium. Bubba Coach and the personalised Guidance panel are Premium features. OBubba unlocks Premium during pregnancy and through the first two corrected-age months; plan options follow after that early-free period.
Build a calmer feeding handover → — keep bottle, breast, pumping, nappies, growth and shared-carer context in one feeding record that knows when not to judge from millilitres alone.
What not to do
- Do not hold the teat in a closed or crying mouth.
- Do not repeatedly reinsert the bottle after clear refusal.
- Do not wait until extreme hunger to make acceptance “inevitable”.
- Do not prop the bottle or leave baby alone with it.
- Do not enlarge the teat hole.
- Do not keep changing formula without advice.
- Do not log prepared milk as milk taken.
- Do not use solids to compensate for refused milk in a baby under 12 months.
Responsive feeding is not permissive or vague. It is close observation plus a firm commitment not to override the baby's stop cues.
When to seek help
Contact your midwife, health visitor, GP or NHS 111 promptly if your baby:
- suddenly refuses their usual milk feeds
- has difficulty feeding or seems in pain
- repeatedly coughs, chokes or changes colour during feeds
- is vomiting repeatedly or cannot keep feeds down
- has fewer wet nappies than usual
- is unusually sleepy, floppy or difficult to wake
- is not gaining weight as expected
- has breathing difficulty or seems seriously unwell
The NHS reflux guidance recommends professional advice when a baby has difficulty feeding, refuses feeds or repeatedly vomits and seems uncomfortable.
Call 999 for severe breathing difficulty, blue or grey colour, unresponsiveness, collapse or another life-threatening emergency.
Frequently asked questions
Why does my breastfed baby refuse a bottle?
A bottle is a different oral skill and sensory experience. Timing, carer, position and flow may all matter. It does not mean your baby is being difficult or that breastfeeding caused a problem.
Should I offer a bottle when my baby is very hungry?
No. NHS guidance suggests trying when baby is calm and happy. Extreme hunger makes learning an unfamiliar feeding method harder and increases pressure for everyone.
How long should I keep trying in one session?
There is no required duration. Stop when your baby repeatedly turns away, pushes the bottle or becomes distressed. Several brief, calm experiences are more useful than one long battle.
Will a faster-flow teat solve bottle refusal?
Not necessarily. A baby frustrated by slow flow may benefit from assessment, but a fast flow can cause coughing, gulping and milk loss. Match the teat to your baby's skills with professional help if feeding remains difficult.
Should the breastfeeding parent leave the house?
Usually that is unnecessary. Another familiar adult can try while the breastfeeding parent steps into another room. The goal is a different cue pattern, not a stressful separation.
Can I log a refused bottle in OBubba?
Log the amount actually taken as the bottle feed. Put prepared/offered amounts and the response in the note. If no milk was taken, use a standalone note so a failed attempt does not count as a completed milk feed.
What if my baby takes bottles at nursery but not at home?
That shows the skill exists and context matters. Ask nursery about position, timing, teat, movement and break cues. You do not need to reproduce every detail if home breastfeeding continues to work for your family.
Ready to try OBubba?
Use OBubba to track feeds, sleep, naps, nappies, growth, milestones and family handovers in one calm baby tracker app.